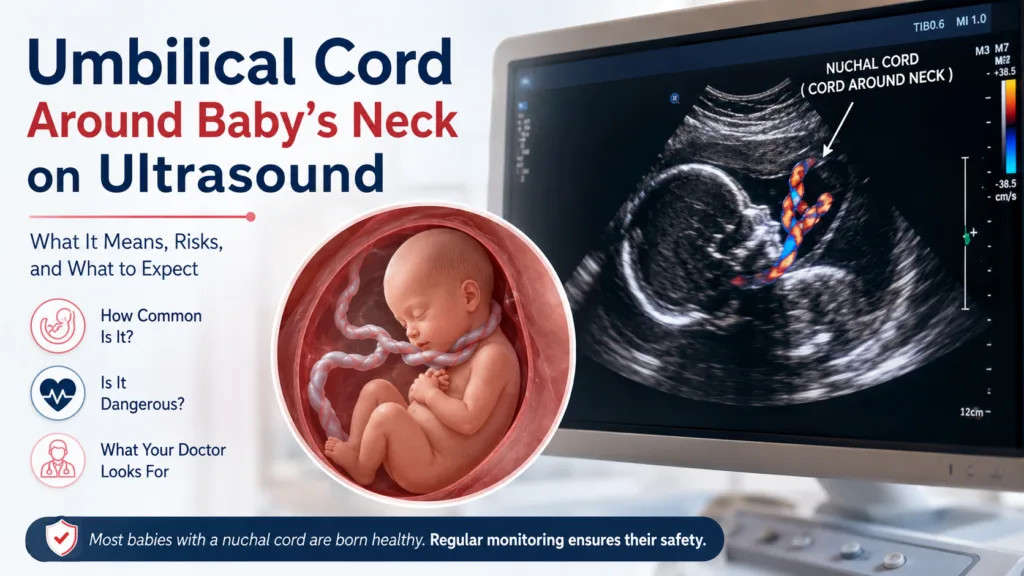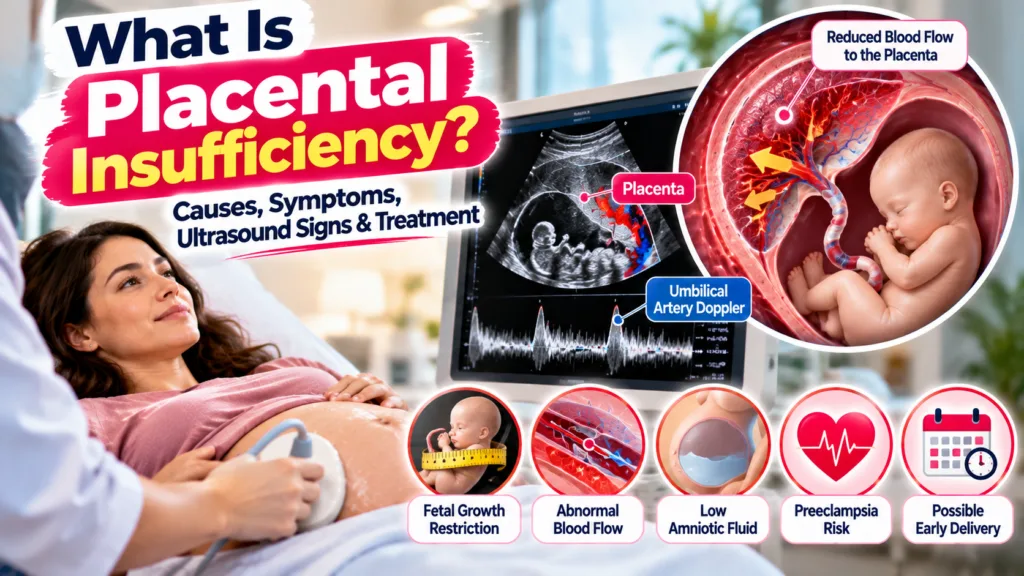
Placental insufficiency is a pregnancy condition in which the placenta does not provide the fetus with enough oxygen and nutrients. It is often associated with fetal growth restriction (FGR), abnormal blood flow on Doppler ultrasound, preeclampsia, low amniotic fluid, and other pregnancy complications.
The term can sound alarming, but placental insufficiency is not diagnosed from one ultrasound measurement alone. There is no single universally accepted test that confirms it. Healthcare professionals usually look at the baby’s growth, placental function, Doppler blood flow, amniotic fluid, maternal health, and overall pregnancy history to determine whether placental dysfunction may be affecting the pregnancy.
What Is Placental Insufficiency?
The placenta is a temporary organ that develops during pregnancy. It connects the mother and fetus and plays an essential role in supplying oxygen and nutrients while removing waste products.
Placental insufficiency, also called uteroplacental insufficiency or placental dysfunction, refers to inadequate placental function or blood flow that results in insufficient delivery of oxygen and nutrients to the fetus.
The condition can develop because of abnormal placental development, impaired blood flow to the placenta, maternal medical conditions, placental injury, or other pregnancy-related factors.
One of the most important consequences is fetal growth restriction, where the fetus does not reach its expected growth potential.
However, an important distinction is that not every small baby has placental insufficiency.
Some babies are constitutionally small but healthy. Healthcare professionals therefore use fetal growth patterns, Doppler findings, maternal conditions, and other evidence to determine whether a small fetus may have an underlying placental problem.
What Does the Placenta Do During Pregnancy?
The placenta performs several critical functions.
It helps:
- Deliver oxygen to the fetus
- Transport nutrients
- Remove fetal waste products
- Produce pregnancy-related hormones
- Support the maternal-fetal exchange of blood and nutrients
For this system to work properly, maternal blood must reach the placenta through the uterine circulation and exchange oxygen and nutrients efficiently.
If placental blood flow becomes inadequate, the fetus may receive less oxygen and nutrition than it needs.
Over time, the fetus may respond by slowing growth or redistributing blood flow toward vital organs. These changes can sometimes be detected through ultrasound and Doppler studies.
What Causes Placental Insufficiency?
There is not always one identifiable cause.
Placental dysfunction can develop because of problems involving placental development, maternal blood flow, blood vessels, inflammation, or other pregnancy conditions.
Potential contributors include:
High Blood Pressure and Preeclampsia
Hypertension and preeclampsia can affect blood flow to the placenta and are strongly associated with placental dysfunction and fetal growth restriction.
Diabetes
Preexisting diabetes and other vascular conditions may increase the risk of placental and pregnancy complications.
Abnormal Placental Development
If the placenta does not develop or attach normally, blood flow and nutrient exchange may be affected.
Placental Abruption
When the placenta separates partially or completely from the uterine wall before delivery, the exchange of oxygen and nutrients can be compromised.
Blood-Clotting Disorders
Certain thrombophilias and autoimmune conditions may affect placental blood vessels.
Smoking, Alcohol and Certain Drugs
Tobacco exposure and certain substance exposures during pregnancy can negatively affect placental function.
Other Conditions
Chronic vascular disease, kidney disease, autoimmune disease, severe nutritional problems, multiple pregnancy, and certain medications may also be associated with abnormal placental function.
Sometimes, however, no specific cause can be identified.
Who Is at Higher Risk?
Risk may be higher in people with:
- Previous pregnancy complicated by fetal growth restriction
- Previous preeclampsia
- Chronic hypertension
- Diabetes with vascular complications
- Kidney disease
- Autoimmune disease
- Certain blood-clotting disorders
- Previous placental abruption
- Smoking during pregnancy
- Multiple pregnancy
- Certain uterine or placental abnormalities
Having a risk factor does not mean placental insufficiency will definitely develop.
What Are the Symptoms of Placental Insufficiency?
One of the challenging aspects of placental insufficiency is that there may be no obvious maternal symptoms.
The first indication may come from a routine prenatal examination or ultrasound.
Possible warning signs include:
Baby Measuring Smaller Than Expected
A fundal-height measurement that is smaller than expected may lead a healthcare professional to order an ultrasound to evaluate fetal growth.
Decreased Fetal Movement
A noticeable decrease in fetal movement can be a warning sign that requires prompt evaluation.
However, reduced movement can have many causes and should not automatically be attributed to placental insufficiency.
Vaginal Bleeding
Bleeding during pregnancy can occur for many reasons, including placental problems. Any unexplained bleeding during pregnancy should be discussed with a healthcare professional.
Maternal Symptoms of Preeclampsia
If placental dysfunction is associated with preeclampsia, symptoms may include severe headache, vision changes, upper abdominal pain, sudden swelling, or high blood pressure.
These symptoms require medical evaluation.
Can Ultrasound Detect Placental Insufficiency?
Ultrasound can identify findings that raise concern for placental dysfunction, but there is no single ultrasound measurement that diagnoses placental insufficiency in every pregnancy.
Ultrasound may evaluate:
- Estimated fetal weight
- Abdominal circumference
- Fetal growth over time
- Amniotic fluid
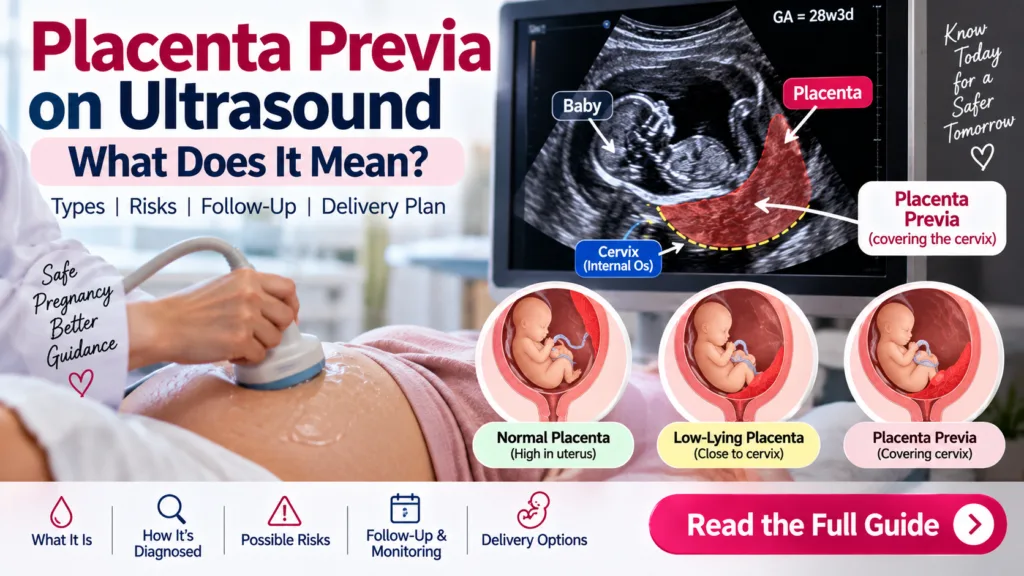
- Placental location and appearance
- Umbilical cord
- Doppler blood flow
The baby’s growth is particularly important.
In the United States, fetal growth restriction is commonly defined as an estimated fetal weight or abdominal circumference below the 10th percentile for gestational age.
But a fetus below the 10th percentile is not automatically suffering from placental insufficiency.
The overall clinical picture matters.
What Does Placental Insufficiency Look Like on Ultrasound?
There is no single classic ultrasound appearance.
Instead, healthcare professionals may see a combination of findings suggesting that the placenta may not be functioning adequately.
1. Fetal Growth Restriction
The fetus may measure smaller than expected for gestational age.
Serial ultrasounds are particularly useful because they show whether the fetus continues to grow appropriately.
2. Low Amniotic Fluid
Placental dysfunction can be associated with reduced fetal urine production and therefore lower amniotic fluid.
Oligohydramnios can have other causes, however, so it is not specific for placental insufficiency.
3. Abnormal Doppler Flow
Doppler ultrasound can evaluate blood flow through vessels such as the umbilical artery.
Abnormal umbilical artery Doppler findings can indicate increased resistance in the placental circulation, particularly when fetal growth restriction is present.
4. Abnormal Fetal Growth Pattern
A fetus may initially measure normally but later show slowing growth.
This is why comparing current measurements with previous ultrasounds can be valuable.
Doppler Ultrasound and Placental Blood Flow
Doppler ultrasound is one of the most important tools used when fetal growth restriction and possible placental dysfunction are suspected.
The umbilical artery Doppler evaluates blood flow from the fetus toward the placenta.
Normally, blood continues to flow forward during diastole.
As placental vascular resistance increases, the diastolic component may decrease.
In more severe cases, Doppler can show:
- Increased resistance
- Decreased end-diastolic flow
- Absent end-diastolic velocity (AEDV)
- Reversed end-diastolic velocity (REDV)
Absent or reversed end-diastolic flow is concerning and requires close maternal-fetal assessment.
SMFM recommends serial umbilical artery Doppler assessment after FGR is diagnosed, with frequency depending on the severity and Doppler findings.
What About Uterine Artery Doppler?
Uterine artery Doppler evaluates blood flow through the maternal uterine circulation.
Abnormal findings can be associated with impaired placentation and increased risk of conditions such as preeclampsia and fetal growth restriction.
However, uterine artery Doppler is not a standalone diagnostic test for placental insufficiency.
Placental Insufficiency and Fetal Growth Restriction
The two conditions are closely related, but they are not exactly the same.
Placental insufficiency is a possible underlying cause of FGR.
FGR means the fetus is not achieving its expected growth potential.
SMFM recommends defining FGR in the United States using an estimated fetal weight or abdominal circumference below the 10th percentile for gestational age.
The important question is whether the small size represents:
A healthy constitutionally small fetus
or
Pathologic growth restriction related to placental, maternal, or fetal problems.
Doppler studies, serial growth measurements, maternal conditions, amniotic fluid, and fetal surveillance can help healthcare professionals make this distinction.
Placental Insufficiency and Amniotic Fluid
Low amniotic fluid, called oligohydramnios, can occur in pregnancies affected by placental dysfunction.
When the placenta does not provide adequate blood flow, fetal blood flow to the kidneys may decrease. This can reduce fetal urine production and consequently decrease amniotic fluid.
But low amniotic fluid is not specific to placental insufficiency.
Other causes include:
- Rupture of membranes
- Certain fetal kidney or urinary tract abnormalities
- Placental problems
- Some medications
- Post-term pregnancy
Therefore, the cause of low amniotic fluid needs to be investigated.
Can Placental Insufficiency Improve?
There is no medication that can simply “repair” a placenta that is already functioning inadequately.
However, the pregnancy can often be carefully managed to reduce risks.
Management may include:
- Treating maternal hypertension
- Monitoring fetal growth
- Doppler ultrasound
- Nonstress testing
- Biophysical profiles
- Monitoring fetal movement
- Monitoring amniotic fluid
- Managing diabetes and other maternal conditions
- Planning delivery at the appropriate time
The goal is to balance two competing risks:
Keeping the fetus in the uterus long enough to mature
versus
Delivering before placental function becomes unsafe.
How Is Placental Insufficiency Managed?
Treatment is individualized according to gestational age, fetal growth, Doppler findings, maternal health, and other pregnancy factors.
Regular Ultrasound Monitoring
Serial ultrasound may be used to track fetal growth and amniotic fluid.
Umbilical Artery Doppler
When FGR is diagnosed, umbilical artery Doppler is an important surveillance tool. SMFM recommends repeated Doppler assessment, with more frequent monitoring when abnormal flow is present.
Nonstress Test
A nonstress test evaluates the fetal heart rate and its response to fetal movement.
Biophysical Profile
A BPP combines ultrasound observations with fetal heart-rate assessment to evaluate fetal well-being.
ACOG lists nonstress testing, biophysical profiles, fetal movement assessment, and umbilical artery Doppler among the tools used for antenatal fetal surveillance.
Treating Maternal Conditions
Controlling conditions such as hypertension, diabetes, or other medical disorders is an important part of pregnancy management.
When Might Early Delivery Be Recommended?
If the placenta is no longer adequately supporting the fetus, continuing the pregnancy may eventually become more dangerous than delivery.
The timing depends on:
- Gestational age
- Fetal growth
- Umbilical artery Doppler
- Fetal heart-rate testing
- Amniotic fluid
- Maternal blood pressure
- Preeclampsia or other complications
- Overall fetal condition
For example, SMFM recommends different delivery timing depending on the severity of FGR and umbilical artery Doppler findings. Pregnancies with reversed end-diastolic flow require particularly intensive management.
There is no single delivery week that applies to every pregnancy with placental insufficiency.
Can Placental Insufficiency Be Prevented?
Not every case can be prevented.
However, reducing preventable risk factors and receiving regular prenatal care can help identify problems earlier.
Helpful steps include:
- Attend regular prenatal appointments
- Avoid smoking
- Avoid alcohol and recreational drugs during pregnancy
- Control chronic medical conditions
- Take prescribed prenatal vitamins
- Discuss medications with your healthcare professional
- Monitor blood pressure when recommended
- Report decreased fetal movement promptly
- Follow recommended ultrasound and fetal surveillance schedules
What About Low-Dose Aspirin?
Low-dose aspirin is recommended for certain pregnant individuals at increased risk of preeclampsia.
It is not a treatment for established placental insufficiency and is not recommended solely to prevent recurrent fetal growth restriction in people without preeclampsia risk factors.
Do not start aspirin during pregnancy without discussing it with your healthcare professional.
When Should You Contact Your Doctor?
Contact your pregnancy care team promptly if you notice:
- A significant decrease in fetal movement
- Vaginal bleeding
- Leakage of fluid
- Severe abdominal or pelvic pain
- Severe headache
- Vision changes
- Sudden or significant swelling
- Symptoms associated with high blood pressure
Some pregnancy complications can progress without obvious symptoms, which is why routine prenatal care and recommended fetal surveillance are important.
Medical Disclaimer
This article is for educational and informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Ultrasound and Doppler findings should always be interpreted by a qualified healthcare professional in the context of the complete pregnancy history and clinical findings.
Sources
- American College of Obstetricians and Gynecologists (ACOG) — Fetal Growth Restriction and antenatal fetal surveillance guidance.
- Society for Maternal-Fetal Medicine (SMFM) — Consult Series #52: Diagnosis and Management of Fetal Growth Restriction.
- ACOG — Low-Dose Aspirin Use During Pregnancy.
- Cleveland Clinic — Placental Insufficiency: Causes, Symptoms & Treatment.
- NCBI Bookshelf / StatPearls — Placental Insufficiency.